

Infusion Therapy for Rheumatoid Arthritis: What to Expect at Our Whittier Infusion Center
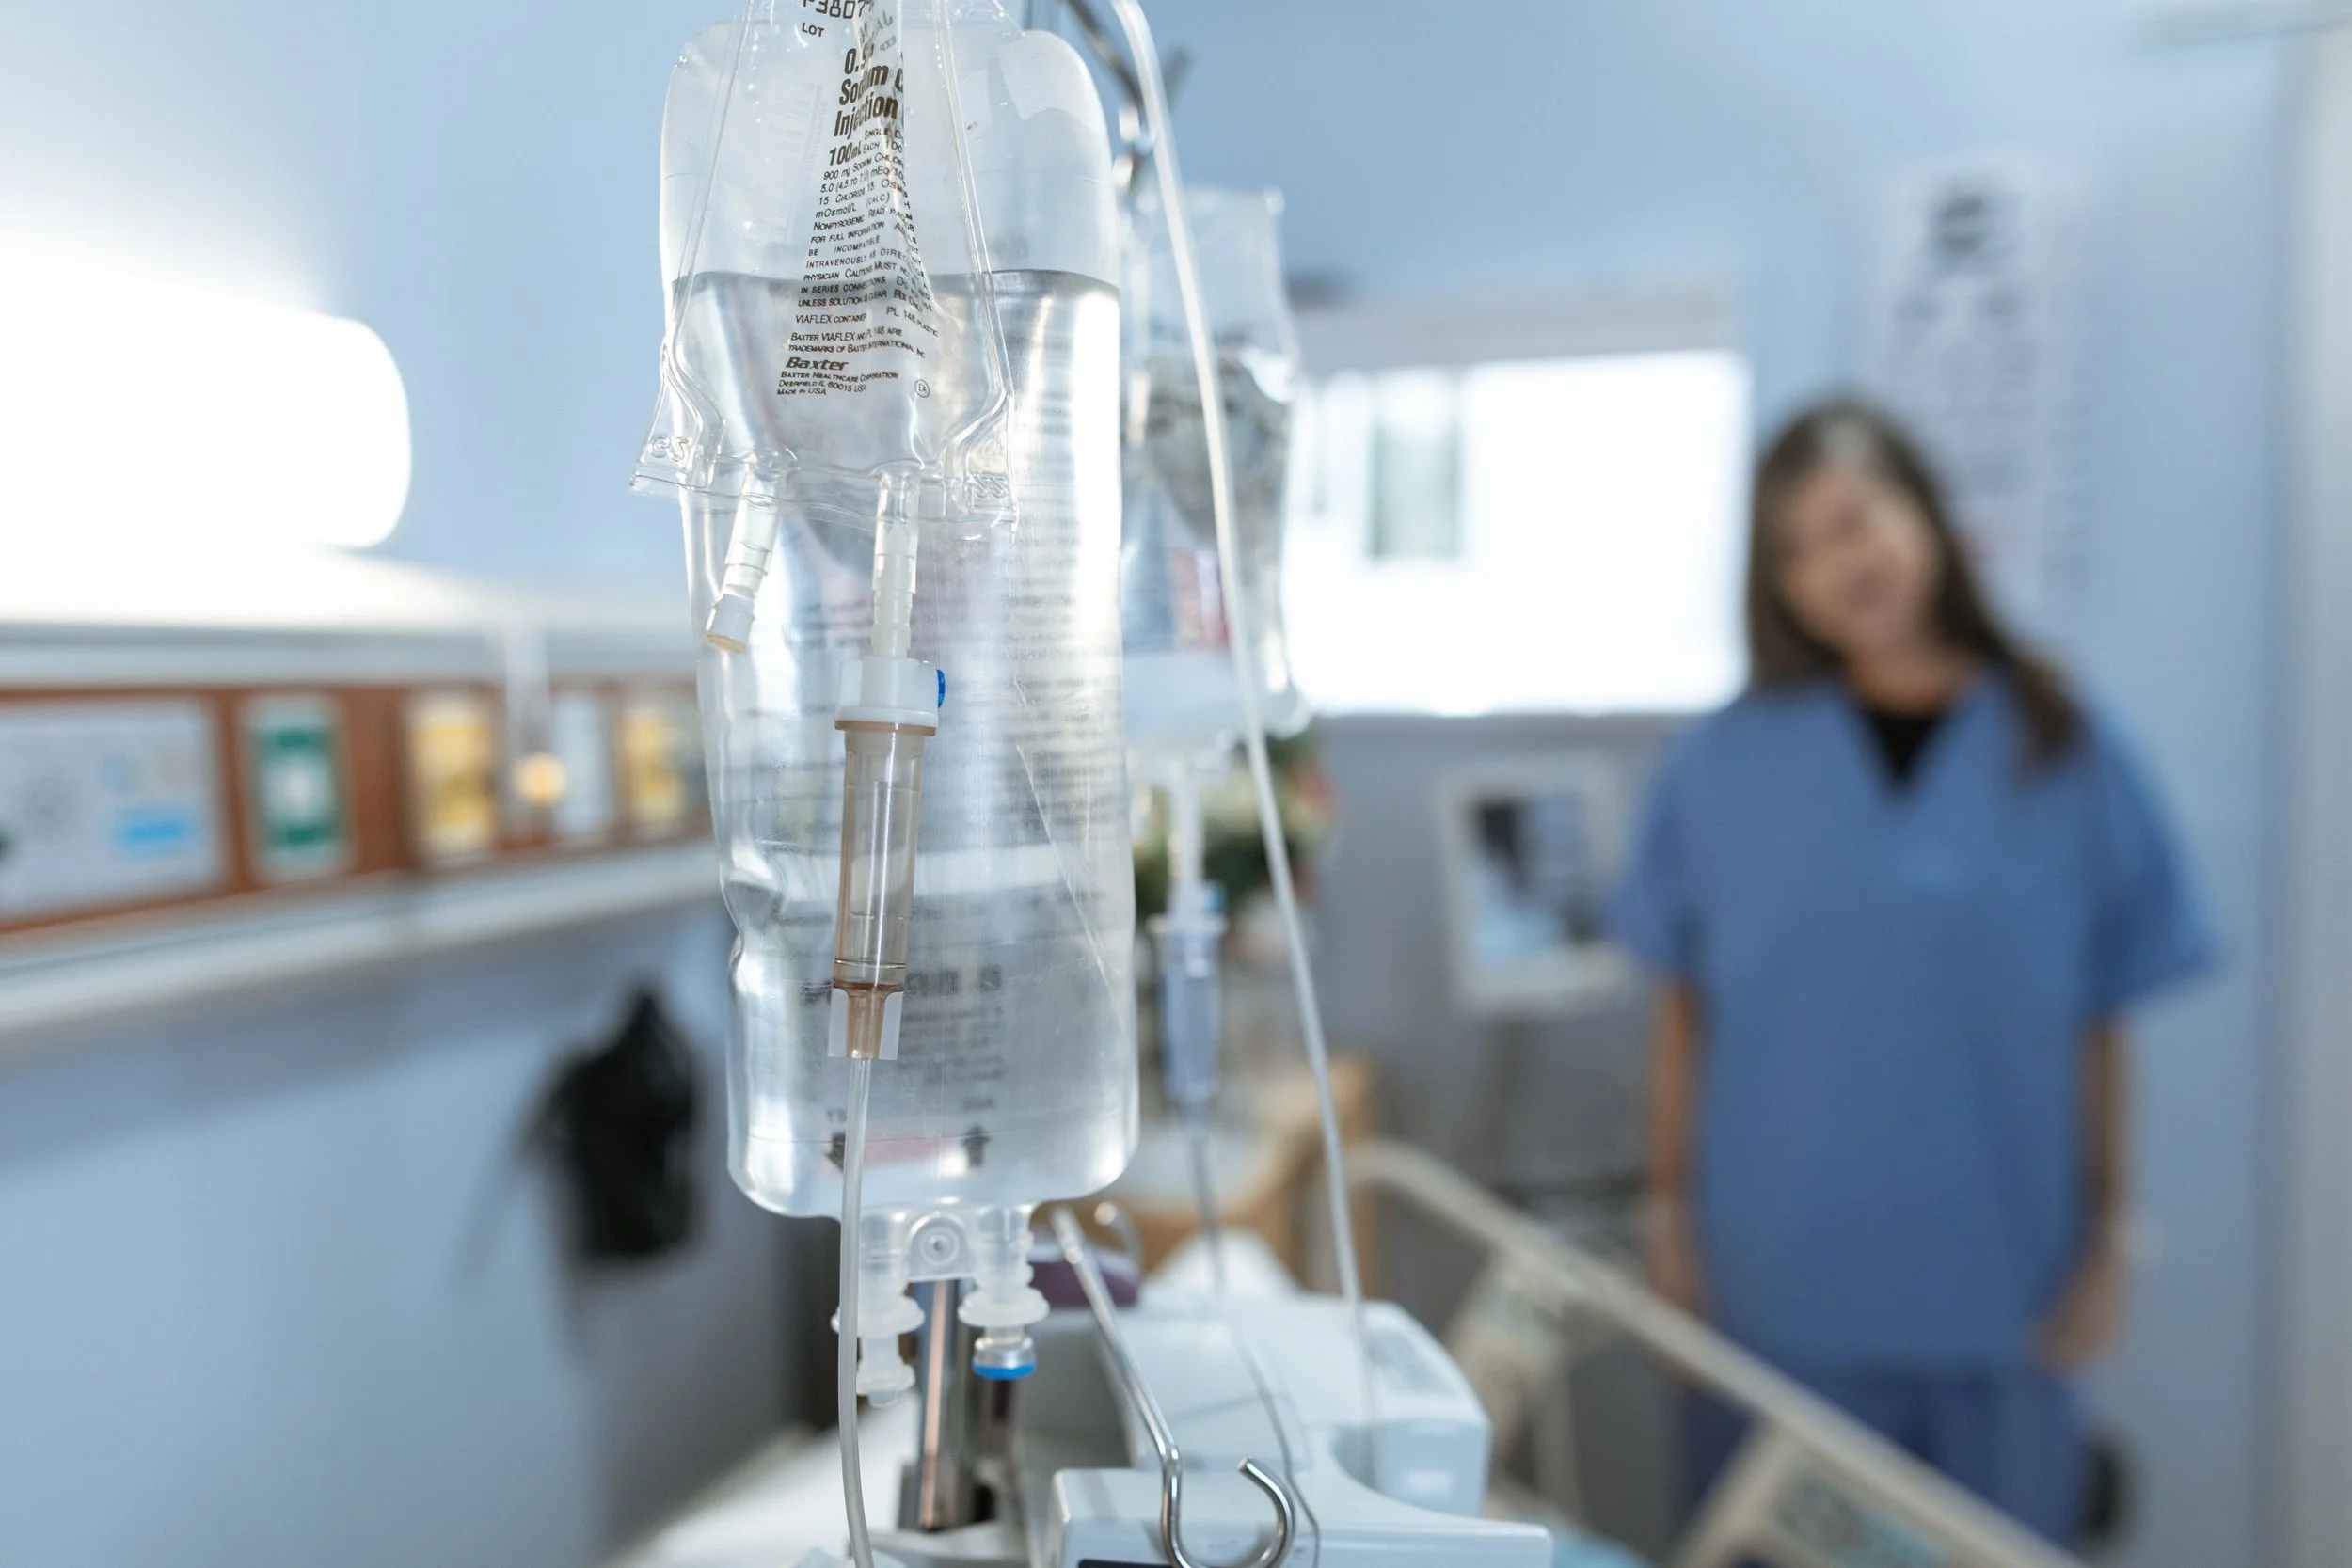
Biologic infusions are given in our in-office infusion center in Whittier, supervised by our rheumatologists.
Infusion therapy for rheumatoid arthritis means receiving a biologic medication through an IV, in a monitored setting, on a schedule that ranges from every few weeks to twice a year depending on the drug. It is usually the next step when pills and self-injections have not controlled the disease. At Amicus Arthritis we give these treatments in our own infusion center inside our Whittier office, supervised by the same rheumatologists who manage your RA. Here is who it is for, what the medications are, what the first day looks like, and how it is covered.
What is infusion therapy for rheumatoid arthritis?
Rheumatoid arthritis is an autoimmune disease in which the immune system attacks the lining of the joints. The most effective treatments are medications that block specific parts of that immune response. Some of these can be taken as tablets and some as injections you give yourself at home. Others are given directly into the bloodstream through an IV line, either because the drug is only made in an IV form or because the dose is too large for a shot. That is infusion therapy.
The medications are called biologics because they are made from living cells rather than synthesized chemically. Each one targets a different signal in the immune system. Johns Hopkins Arthritis Center has a thorough overview of how these treatment classes fit together; the short version is that infusions are one of several ways to deliver the most powerful RA drugs we have.
Who is a candidate for RA infusions?
Most patients start with a conventional disease-modifying drug, usually methotrexate, sometimes combined with others. The 2021 American College of Rheumatology RA guideline recommends adding or switching to a biologic or targeted medication when RA remains active despite an adequate trial of those first-line drugs, usually about three months at a proper dose, or sooner in some cases. Whether that biologic is a pill, a self-injection, or an infusion depends on the specific medication, your other health conditions, your insurance, and your preference.
Infusions tend to be the right fit for patients who would rather not self-inject, who have trouble remembering frequent doses, whose insurance covers physician-administered medications more fully, or who need a drug that only comes in IV form. Some patients with RA that has resisted several other biologics do best on an infused medication with a different mechanism. This is a decision we make together at a rheumatoid arthritis visit, not a default.
Infusion medications used for rheumatoid arthritis
These are the IV biologics most often used for RA. The schedules below are typical maintenance schedules; loading doses at the start are often closer together, and your rheumatologist sets the exact plan.
Infliximab (Remicade and biosimilars such as Inflectra, Renflexis, Avsola): Blocks TNF, a major inflammation signal. Three starting doses over six weeks, then about every eight weeks, given with methotrexate; some patients need a higher dose or more frequent infusions. IV only for RA.
Abatacept (Orencia): Interrupts T-cell activation. Starting doses at weeks 0, 2 and 4, then about once a month. Also available as a self-injection.
Tocilizumab (Actemra and biosimilars): Blocks the IL-6 signal. About once a month. Also available as a self-injection.
Golimumab (Simponi Aria): Blocks TNF. About every eight weeks after loading doses, given with methotrexate. Also available as a self-injection.
Rituximab (Rituxan and biosimilars): Reduces B cells. Approved for RA after at least one TNF blocker has not worked, and given with methotrexate. A course of two infusions two weeks apart, then repeat courses about every six months and no sooner than every sixteen weeks. IV only.
What a first infusion day looks like at our Whittier office
Before your first infusion we review your labs, confirm that screening for tuberculosis and for hepatitis B and C is complete, bring your vaccines up to date, and talk through pregnancy and family planning, since some biologics are fine in pregnancy and some are not, and make sure insurance authorization is in hand. You do not have to chase any of that; our staff does.
On the day, you check in at our regular front desk, not a hospital. A nurse takes your vitals, places a small IV in your arm or hand, and may give a premedication such as an antihistamine or acetaminophen to reduce the chance of a reaction, and a steroid before every rituximab infusion. The medication then runs slowly through the line while you sit in a reclining chair. Depending on the drug, that takes anywhere from about half an hour to several hours, and a first rituximab infusion can run four to six hours or more, and some drugs require a short observation period afterward. Bring a book, a charger, and a snack. For a first infusion, or any infusion with an IV antihistamine, bring a driver, since those medications often cause drowsiness. Otherwise most patients drive themselves home; we will tell you ahead of time if your premedication means you should not.
A rheumatologist is on site during infusions. Your infusion nurse responds first if anything feels off, slowing or stopping the drip, and the physician who manages your RA is steps away rather than on the other end of a phone call.
One building. Diagnosis, lab draws, imaging, joint injections, clinical trials, and infusions all happen inside our Whittier office. Many patients have to travel to separate locations for these services.
Wondering whether infusion therapy is the next step for your RA? Bring your current medication list and recent labs. We will walk through the options, the schedule, and what your plan covers before anything is decided. Call (562) 758-6600 or request an appointment online.
Infusions vs. self-injections vs. pills
Pills are the simplest to take and the easiest to forget. The targeted oral drugs, the JAK inhibitors such as tofacitinib and upadacitinib, carry an FDA boxed warning covering heart problems, blood clots, cancer and serious infections, particularly in people over 50 with heart risk factors, so they come with their own monitoring. Self-injections offer flexibility and independence, but they require you to be comfortable with a needle and to keep the medication refrigerated and on schedule. Infusions trade convenience at home for certainty: the dose is given by a nurse, documented, and observed, and you only have to think about it every few weeks to every few months, depending on the drug.
None of these routes is better in the abstract. What matters is which medication controls your disease with the fewest side effects, and which one you will actually take consistently for years. Consistency is what protects the joints.
Side effects and how we monitor for them
The most common problem is an infusion reaction: flushing, itching, headache, or nausea during or shortly after the infusion. Most are mild and settle by slowing the drip or adding a premedication. Serious allergic reactions are uncommon, and that is exactly why infusions are given with a nurse present and emergency medication on hand. Infliximab can also cause a delayed reaction, with joint pain, rash or fever three to twelve days afterward, so call us if that happens. Tocilizumab carries a risk of bowel tears, especially with a history of diverticulitis, and it can keep fever and the CRP blood test from rising, which can hide an infection. Rituximab carries a risk of hepatitis B reactivating and, rarely, a serious brain infection called PML. Call us before any surgery or dental procedure, since infusion timing may need to shift, and plan on a yearly skin check, because some biologics slightly raise skin cancer risk.
Because every biologic quiets part of the immune system, infections are the main long-term risk. That is why we screen for tuberculosis and hepatitis B before starting, review vaccines, check labs on a regular schedule, and ask you to call us about any fever, cough, or wound that is not healing. Some medications have additional monitoring, for example blood counts, liver tests, and cholesterol with tocilizumab. We go through the specific list for your drug before the first dose.
In-office infusion center vs. hospital outpatient infusion
The same medication can be given in a hospital outpatient department, a standalone infusion company, or a rheumatologist’s office. The drug is identical. What differs is cost, convenience, and who is watching. Hospital-based infusion typically carries facility charges that independent offices do not, which can mean a higher bill for the same treatment, especially on plans with coinsurance. Standalone infusion centers can be convenient but may be separate from the doctor who prescribed the treatment.
In our office, the nurse giving your infusion knows your history, the physician who prescribed it is down the hall, and any dose change, lab result, or flare is handled in the same visit. Scheduling is direct, parking is free, and you are not navigating a hospital campus while your joints are sore.
Insurance, Medicare Part B, and prior authorization
Infused biologics are physician-administered drugs, which changes how they are covered. For patients on Original Medicare, drugs given in a doctor’s office generally fall under Part B rather than the Part D prescription plan; Medicare’s guide to outpatient prescription drug coverage explains the distinction, and Part B generally leaves the patient responsible for twenty percent of the drug cost, which is substantial for a biologic, though a Medicare supplement plan often covers that remaining share. Medicare Advantage and commercial plans cover infusions too, but nearly all of them require prior authorization, which means documentation that first-line treatment was tried.
Our staff handles the authorization, verifies your benefits, and tells you what to expect before your first infusion. Most manufacturers also offer copay assistance programs for commercially insured patients, and we help with those applications. Federal law prevents those copay cards from being used with Medicare, Medicare Advantage or Medi-Cal; independent charitable foundations are the route there instead. Two other things shape access: many plans require step therapy, meaning you try less expensive drugs first, and many now require a biosimilar, which is why a drug may be switched. Biosimilars work as well as the original. If cost is the barrier between you and a treatment that works, say so, because there is usually a path.
We accept Medicare, Medi-Cal, and most PPO, HMO, and IPA plans.
Infusion therapy in Whittier, the San Gabriel Valley, and Southeast LA
Amicus Arthritis & Osteoporosis Center is an independent rheumatology practice at 12456 Washington Blvd in Whittier, with patients coming from El Monte, Temple City, Alhambra, Rowland Heights, Diamond Bar, Montebello, Pico Rivera, Downey, Santa Fe Springs, and Norwalk. Our rheumatologists see patients in English, and several also in Spanish, Mandarin, or Farsi. Because we also run clinical trials in rheumatoid arthritis, patients here sometimes have access to newer therapies before they are widely available.
If your RA is still active on your current treatment, or your current infusion arrangement is not working for you, we are glad to take a look. Directions and parking are here.
Frequently asked questions
What is the best infusion for rheumatoid arthritis?
There is no single best one. Infliximab, abatacept, tocilizumab, golimumab, and rituximab each target a different part of the immune system, and the right choice depends on what you have tried, your other health conditions, and your insurance. A rheumatologist chooses based on your history, and it is common to switch if the first one does not control the disease.
Are infusions better than injections for rheumatoid arthritis?
Not inherently. For the drugs that come both ways, abatacept, tocilizumab and golimumab, the two routes are equally effective. Infliximab and rituximab are given only by IV for RA. Infusions are given less often and are observed by a nurse, which some patients prefer. Self-injections offer more independence. The decision comes down to the specific drug, your comfort with self-injecting, and your coverage.
How long does an RA infusion take?
Depending on the medication, the infusion itself takes roughly thirty minutes to a few hours, plus time for check-in and, for some drugs, a short observation period afterward. Golimumab and abatacept are the shortest at about thirty minutes, and tocilizumab runs about an hour. Rituximab is the longest, and a first rituximab visit often takes most of the day. For the other drugs, plan on a half day for your first visit and less for later ones.
Do infusions work for rheumatoid arthritis?
For patients whose RA has not responded adequately to methotrexate and similar drugs, biologic infusions are among the most effective treatments available and can bring the disease into low activity or remission for many people. Response is usually judged over the first few months, and we adjust if the improvement is not enough.
Does Medicare cover infusion therapy for rheumatoid arthritis?
Generally yes. Biologics given in a doctor’s office are usually covered under Medicare Part B as physician-administered drugs, with a supplement plan covering the remaining share for many patients. Medicare Advantage plans cover them as well but typically require prior authorization. Our staff verifies your specific coverage before treatment starts.
Call (562) 758-6600 to ask about infusion therapy at our Whittier office.
This article is for general educational purposes and does not replace personalized medical advice. If you have a fever with a hot, swollen joint, or symptoms that are getting worse quickly, seek urgent care.