

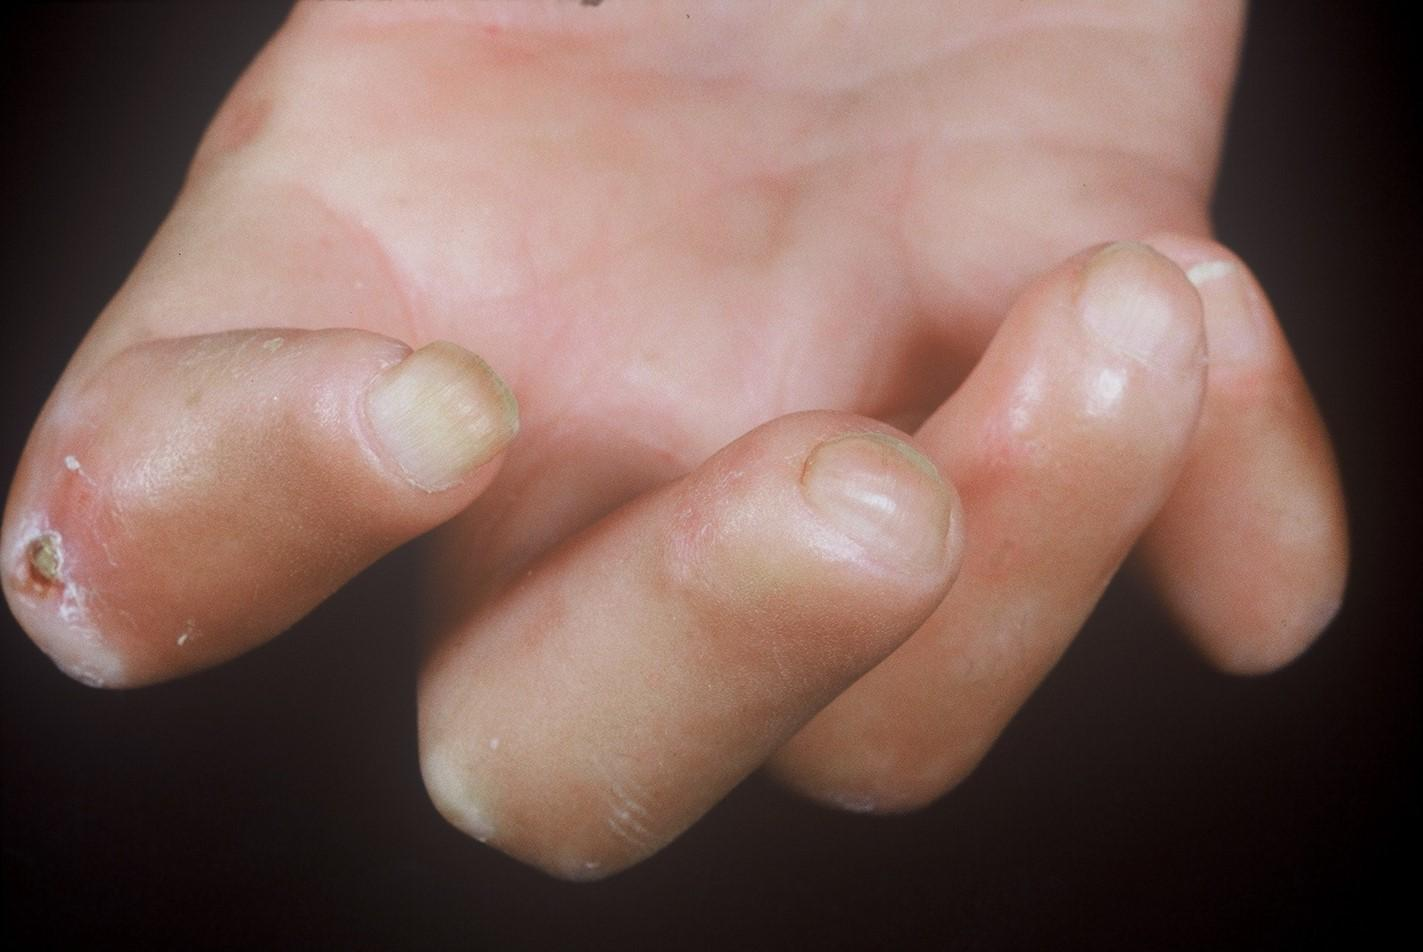
Systemic sclerosis (SSc) is an autoimmune connective-tissue disease characterized by vasculopathy, immune dysregulation, and variable skin and internal-organ fibrosis. Early recognition is important because pulmonary, cardiac, renal, and gastrointestinal involvement may occur before significant symptoms develop.
Systemic Sclerosis: PCP Quick Guide
Suspect systemic sclerosis when Raynaud’s is accompanied by puffy fingers or sclerodactyly (tight, shiny, thickened finger skin).
Other clues: digital ulcers/pitting, telangiectasias, calcinosis cutis, GERD/dysphagia, dyspnea, or dry cough.
Check ANA and SSc-specific antibodies: anti-centromere, anti-Scl-70/topoisomerase I, and anti-RNA polymerase III.
Raynaud’s + sclerodactyly/puffy fingers + positive ANA or SSc-specific antibodies should prompt rheumatology referral.
When to Suspect Systemic Sclerosis
Consider SSc in a patient with Raynaud’s phenomenon plus one or more of the following:
Puffy fingers progressing to sclerodactyly or skin thickening
Digital pitting scars, fingertip ulcers, or recurrent digital ischemia
Abnormal nailfold capillaries
Telangiectasias
Calcinosis
New or significant GERD, dysphagia, or esophageal dysmotility
Unexplained dyspnea, dry cough, or reduced exercise tolerance
Pulmonary hypertension
Unexplained inflammatory arthritis or tendon friction rubs
SSc-associated autoantibodies
Red flags for early rheumatology referral: new-onset Raynaud’s in adulthood accompanied by puffy/tight fingers, digital ulcers, abnormal nailfold findings, or a positive SSc-specific antibody.
Initial Diagnostic Evaluation
There is no single diagnostic blood test for systemic sclerosis. Diagnosis is clinical and supported by examination, serology, nailfold findings, and organ assessment.
Suggested initial laboratory evaluation:
ANA with reflex testing/pattern when available
SSc-specific antibodies, particularly:
Anti-centromere
Anti-topoisomerase I (Scl-70)
Anti-RNA polymerase III
CBC
CMP/creatinine
Urinalysis
ESR/CRP as clinically indicated
CK if muscle weakness or suspected myositis is present
The 2013 ACR/EULAR classification criteria incorporate skin thickening, sclerodactyly/puffy fingers, fingertip lesions, telangiectasias, abnormal nailfold capillaries, pulmonary arterial hypertension or interstitial lung disease, Raynaud’s phenomenon, and SSc-associated antibodies. These are classification criteria rather than a substitute for clinical diagnosis.
Baseline Organ Screening
Once SSc is suspected or established, evaluate for clinically silent organ involvement.
Pulmonary
Pulmonary function tests, including FVC and DLCO
High-resolution CT (HRCT) chest to assess for interstitial lung disease when appropriate
Ask about dyspnea, cough, and exercise intolerance
Pulmonary hypertension / cardiac
Echocardiogram
Consider BNP or NT-proBNP as part of PAH assessment
ECG and additional cardiac evaluation when indicated
Renal
Blood pressure at every visit
Creatinine/eGFR
Urinalysis
Educate higher-risk patients regarding home blood-pressure monitoring
Gastrointestinal
Assess for GERD, dysphagia, early satiety, bloating, constipation, diarrhea, and weight loss
Further GI testing based on symptoms
Treatment Overview
Treatment is organ-directed rather than one-size-fits-all.
Raynaud’s phenomenon
Cold avoidance and smoking/nicotine cessation
Dihydropyridine calcium-channel blockers, typically first-line
PDE-5 inhibitors or other vasodilator strategies for refractory disease
Digital ulcers / ischemia
Vasodilator therapy
PDE-5 inhibitors and/or prostacyclin-based therapy in selected severe cases
Urgent specialty assessment for threatened digit or critical ischemia
Skin fibrosis
Immunomodulatory therapy may be appropriate for progressive disease; options commonly include mycophenolate, with other agents selected according to phenotype and organ involvement.
SSc-associated interstitial lung disease
Mycophenolate is commonly used as a first-line immunosuppressive option.
Other selected therapies may include rituximab, tocilizumab, cyclophosphamide, and/or nintedanib, depending on disease phenotype, severity, and progression.
GERD / esophageal disease
Proton-pump inhibitor therapy when indicated
Reflux precautions and evaluation for significant dysmotility or refractory symptoms
Pulmonary arterial hypertension
Requires specialty evaluation and PAH-directed therapy.
Scleroderma renal crisis
Medical emergency.
ACE inhibitor therapy should be initiated promptly when renal crisis is diagnosed.
Systemic glucocorticoids, particularly higher doses, should be used cautiously in SSc because of their association with renal-crisis risk.
Refer Urgently For
New or rapidly worsening dyspnea
Syncope, chest pain, or suspected pulmonary hypertension
Rapidly rising blood pressure or acute kidney injury
New digital ulcer with progressive ischemia
Persistently blue, dusky, or black finger/toe
Rapid progression of skin thickening or systemic symptoms
Clinical pearl: A patient with systemic sclerosis may feel relatively well despite early ILD or pulmonary vascular disease. Baseline and longitudinal organ screening are therefore an essential part of management.
Refer to Amicus Arthritis & Osteoporosis Center
If your patient has suspected or established systemic sclerosis, unexplained Raynaud’s with concerning features, progressive skin tightening, digital ulcers, abnormal SSc serologies, or possible organ involvement, we welcome referrals for rheumatologic evaluation and ongoing care.
Our team can assist with diagnostic confirmation, organ screening, treatment selection, longitudinal monitoring, and coordination with pulmonary, cardiology, nephrology, and gastroenterology when needed.
Amicus Arthritis & Osteoporosis Center
12456 Washington Blvd.
Whittier, CA 90602
Phone: (562) 758-6600
Fax: (562) 758-6709